The argument you’re making has always bothered me because it’s hiding the ball.
If finding something that otherwise carries no symptoms is best left untreated, then the fact that you found it should make no difference to the decision. The doctor should say that the best course of action is to do nothing. More information can never be harmful. If you know information is best not acted on in the abstract, then you also know you should not act on it in particular.
So what you really mean but have left unspoken is one of two things.
First, that doctors are untrustworthy people who make recommendations and decisions based on concerns other than their patient’s wellbeing, such as covering their asses from lawsuits or making more money.
But rather than fix that, you would rather keep patients more ignorant and away from the doctor in the first place. Which actively harms people who do have honest doctors. That is, your approach of not testing hurts people with honest doctors to protect people with dishonest doctors.
Or second, if you take dumb patients as the problem, you are willing to hurt people with good decision making ability (who would heed their good doctor’s advice to leave the possible ailment untreated) so you can protect people with bad decision making.
Because many times, these tests will uncover things that obviously need treatment. They will save many lives. But because more stupid people will hurt themselves, then no one should have access to them.
The political and moral assumptions built into these positions are immense and yet the medical field tucks those away and pretends that this is just a purely scientific truth, that someone running more harmless tests is actually inherently harmful.
>If finding something that otherwise carries no symptoms is best left untreated, then the fact that you found it should make no difference to the decision. The doctor should say that the best course of action is to do nothing. More information can never be harmful.
Absolutely and demonstratively false. There is an entire field of health policy that destroys this harmful idea. First of all, just because something doesn't carry symptoms NOW doesn't mean it won't carry symptoms LATER, but doctors can't always predict this and aren't perfect decision making machines. Many times the patient will push them for further tests and treatment (or the doctors will advocate for it to ease the mind of the patient) which leads to potential harm from unnecessary treatments. And this is just ONE of the ways patients are harmed by unnecessary screening. There is also the psychological damage of having a condition you wouldn't have otherwise known about, and living with that knowledge (take aneurysms for example). Psychological stress has a real physical toll on the body. Then there's the COST associated with unnecessary screening and treatments, which (especially in the US) can run into the thousands quite easily for even simple interventions as a result of unnecessary screening.
Even after that, a screening process can also find something that could be bad, but in some patients doesn't actually decrease their lifespan or quality of life. If we have no way of adjudicating between these cases or predicting which cases will end up bad if left untreated at the present moment, what do you think will happen? People will ask to be treated anyway, and iatrogenics will rear its ugly head.
You cannot ASSUME that screening is automatically good. It must PROVE itself as such in a randomized clinical trial. This trial must show that people live longer and/or better as a result of this intervention. In many well documented cases, this turns out NOT to be the case, which entirely destroys your original rebuttal.
> but doctors can't always predict this and aren't perfect decision making machines
So mass screen healthy people, collect the data, run models, and get better at it. People like you would rather not try, and this is the same reaction I get from doctors. Applying the same tech that we use to improve ad targeting to disease prediction is a no brainer to anyone whose cushy job doesn't depend on the current medieval state of medical technology.
What do you think the entire medical, pharmaceutical, bioinformatic, etc. industries have been doing for decades? Are you really so arrogant to think that other people are too lazy and stupid to think of your brilliant idea and that you are simply more intelligent than everybody else? Do you really think people haven't been trying?
If they aren't mass collecting this data in the first place (for the reasons outlined above), then how can they be doing this?
Or, if they are doing this from quality samples of the population, then we have data to show that, for example, "Yes, Mr. Function Seven, your scan shows elevated levels of Widget-5a enzymes. This is often a precursor to Gadget Cancer, but 30% of the population shows this elevation, while only 1% develop the cancer. It's best to do nothing at this time unless we see further elevation. Have a good day, see you next year"
So either we have this data and we can give accurate advice, or we don't have this data because we're afraid of over-diagnosing non-problems.
I understand the fear, but it's still burying one's head in the sand to not even look.
They are mass collecting the data. They have more data than they know what to do with. Bioinformatics abuses data science at levels comparable to Google and Facebook.
They are getting quality samples from the population. But it's not a simple as "high enzyme = maybe good chance of cancer". How are you going to get those enzymes from their blood in a way that can be applied to the general population? Before that, how do you know there's not confounding factors (of which they are a LOT)?
> So either we have this data and we can give accurate advice, or we don't have this data because we're afraid of over-diagnosing non-problems.
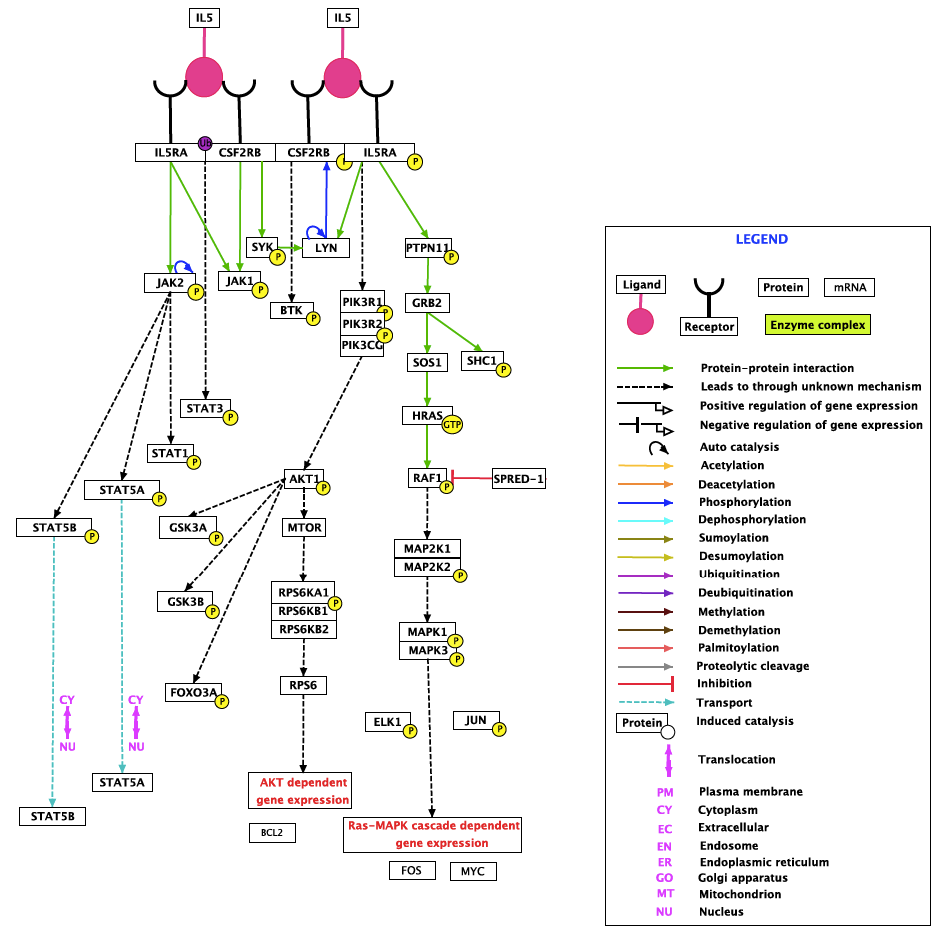
This is what people think the activation of genes is. What they THINK the activation of genes is.
Note the following:
- They don't know all the genes. They are constantly identifying new ones. The number of gene pathways people are pretty sure are complete is small. I don't know if this one is one of the "pretty sure" ones.
- Gene pathways are not just complex in terms of size, they are also non-linear. This is not a computer program, this is a horrible biological mess where biological components constantly and probabilistically emit chemicals.
I don't even think that the pathway I gave you is super representative - it doesn't feature the ridiculous non-linearity and uncertainty that many pathways at the bleeding edge have. They can get much worse.
People are not burying their heads in the sand. They are trying their almighty to dig up from bedrock and reach the sky.
> Bioinformatics abuses data science at levels comparable to Google and Facebook.
To give people a sense of this, it is not unheard of for large scale bioinformatics platforms to set off alarms and/or zone-level capacity issues with the large cloud providers.
> Are you really so arrogant to think that other people are too lazy and stupid to think of your brilliant idea and that you are simply more intelligent than everybody else? Do you really think people haven't been trying?
I find it hard to believe I'm reading this sentiment on HN. Do you realize nearly any disruptive idea has do the "arrogant" thing you are speaking off.
Big companies go out of business all the time, industry disappear or wane all the time, big companies/industries with lots of smart people do stupid stuff on the regular. Characterizing the desire to do something other than status quo as "arrogance" is just the bottom of the barrel. I'm glad Semmelweis didn't think the way you do.
I didn't understand their comment to mean that at all. It's not arrogant to think there might be a better way. It probably is arrogant to think that the better way is actually really simple and easy to implement.
Arrogance definitely can play a big role in success of many startup entrepreneurs. Because they think the answer is simple and their arrogance shields them from not trying. So they go down the road and find out the solution is actually quite complicated, but a small percentage succeed in accomplishing the goal.
> Are you really so arrogant to think that other people are too lazy and stupid to think of your brilliant idea and that you are simply more intelligent than everybody else?
Not OP, but yes, I do.
I've had some runins with the health system. At least the parts that I've seen are worse than the dark ages. Especially endocrinologists have absolutely no clue what they are doing.
The ones I met don't even have superficial knowledge about their full-time job which they've performed for ~20 years.
And yes, this sounds arrogant. I've tripple checked whether I'm just tripping. Their knowledge is not simply outdated, but never correct to begin with.
I think it's a cultural problem which shows in a lot of areas. Medicine doesn't value human life as much as f.e. air transport
You're talking about praxis, we're talking about research. I agree the praxis can be pretty bad, but in regards to the above commenter's remarks on why people don't just simply collect data and apply it, medical professionals simply cannot try out new treatments the way they are suggesting.
To go further, a large issue/distraction in biomedical research has been Big Tech types coming in assuming that the roadblock all along has been lack of smart computational people in the process. I will not name names, but have seen so many instances of personal tech heroes coming in & claiming the underlying problem was that some of the brightest computational I've ever encountered simply didn't know how to computer.
Nothing could be further from the truth. People coming in to "disrupt" only add noise. Eventually those people either understand this and put the effort in to understand the domain or they wander off.
While it’s absolutely true that naive non-experts can end up adding a lot more heat than light, I’ve also seen non-expert people come into stagnant domains and absolutely completely transform and improve upon the state of the art.
I am skeptical of the “more data is bad” meme of screening hesitancy. It cannot be scientifically true in the strictest sense, and to the degree it’s an accurate assertion, it really seems to reveal an unscientificness to how screening data is used today in practice rather than that in principle more data is bad.
In a perfect world you're right. What it's getting at is that screening itself isn't very good in the grand scheme of things, and thus the negatives of extra screening can be argued to be worse than the extra screening. Whether or not that's true, well that's another matter.
The issue in this subthread was the notion that the only thing between the current state of affairs and high quality screening is a bit of disruption. The problem is hard, smart people are working on it, more smart people are always welcome, it'll still take a while.
It's that 1) sometimes collecting the data itself is harmful at scale. E.g. mammography can cause breast cancer, or cause it to spread. 2) the patients actions as a result of the data can, and does at sufficient scale, cause further harm.
> What do you think the entire medical, pharmaceutical, bioinformatic, etc. industries have been doing for decades?
Well, let's remember that the AlphaFold team at Google solved the protein folding problem with a relatively small team in a relatively small number of years after extremely large, well funded companies whose primary business was drug development failed to do so for decades.
So yeah, it's been demonstrated to be possible that the current leaders in a field might be significantly less capable than a different team.
There's confounding here that you're ignoring. For reference, I'm a machine learning research scientist who started in bioinformatics, initially lured by the possibility of a machine learning solution to the protein folding problem.
Google's research arm has made leaps and bounds in a particular field (deep learning) and then managed to apply it successfully to a very, very hard problem (protein folding). That other companies failed to adapt Google's successes in deep learning faster than Google is not surprising at all to me.
One might argue that the impact of academic-big pharma collaboration (in the form of funding for research projects related to CASP) is what enabled a company like Google, with no independent desire to collect the massive amounts of wetlab data required to evaluate or develop a tool like AlphaFold, to even participate.
More importantly, AlphaFold hasn't really solved the protein folding problem well enough for drug development. So, the entire debate might be moot.
> let's remember that the AlphaFold team at Google solved the protein folding problem with a relatively small team in a relatively small number of years after extremely large, well funded companies whose primary business was drug development failed to do so for decades
Did they though? They did extremely well at CASP14, and much better than competing groups. But does this solve protein folding? Deepmind's marketing department would have you think so, but for those of us that work in the field we know that this is not the case.
Furthermore, does protein folding solve the relevant problems of drug design? It solve the forward problem, given an amino acid sequence predict its 3d structure. But for drug design we need the inverse problem, given a specified structure predict an amino acid sequence that produces that structure.
alpha fold was developed at deepmind, not google, they didn't solve the protein folding problem, and it's not surprising that drug discovery companies didn't reach a similar level of accuracy first.
Note that DeepMind drafted off the work of a protein folding guy from academia who had been doing this for decades.
> Are you really so arrogant to think that other people are too lazy and stupid to think of your brilliant idea and that you are simply more intelligent than everybody else?
Here's a report of a person whose wife had seasonal affective disorder. He
- deduced that a powerful enough lightbox should be able to cure SAD
- didn't find any examples of such treatments in literature
- spent $600 to build "LUMINATOR"
- "And as of early 2017, with two winters come and gone, Brienne seems to no longer have crippling SAD—though it took a lot of light bulbs, including light bulbs in her bedroom that had to be timed to go on at 7:30am before she woke up, to sustain the apparent cure."
We have done this for e.g. breast cancer, and that is exactly why people are cautious now, because we have real data on the harm overtesting can cause. That doesn't mean it should never be done, but that it needs to be approached with care.
You are assigning beliefs to me that I do not hold. As I said, we would need a solid randomized controlled clinical trial to determine whether any particular intervention actually helps patients live longer and/or better. That's the only way we know. So go ahead and collect data, do an RCT, and let us know how it goes.
The problem with this and the nnt gatekeeping is that personalized medicine will always require stepping away from massive double blind randomized placebo controlled multiple meta study levels of evidence. From a patient perspective it feels a lot like economics largely determine medical outcomes.
>Many times the patient will push them for further tests and treatment (or the doctors will advocate for it to ease the mind of the patient) which leads to potential harm from unnecessary treatments.
>People will ask to be treated anyway, and iatrogenics will rear its ugly head.
I just want to say that you are in agreement with my position here.
Your point about psychological problems is interesting, but as long as people know what they’re signing up for, it’s okay. Some people aren’t prone to anxiety. Why should they pay the price because other people are? Part of my original point was that implicit in your argument is that people capable of handling it should be denied something because more people incapable of handling it can’t be stopped from hurting themselves. I think many people do not agree with that moral reasoning, so medical people hide it behind objective looking statistics.
And as for cost, I don’t take any arguments from medical people about cost seriously. The reason why costs are so high is because doctors and the medical field as a whole run a massive protectionist racket to keep the supply of medical professionals low.
How fresh of them to say that because they’ve limited the supply of medical resources to enrich themselves, patients must pay by having less access to care.
I think once you become a doctor, you quickly realize that a large amount of the population do not have the temperament to deal with 'maybe' bad news. Many are not the 135 IQ %1 of the population with a low anxiety personality who accept that they will eventually grow old and die, which happens to coincide with many engineering types on HN.
Lol, i would argue that engineers, many of whose primary job function is to imagine worst case scenarios and engineer around those to prevent accidents, data loss, etc. Are the exact type of people that are prone to hypochondria. It's not about growing old and dying, it's about ignoring a stomach ache for a couple months and then being told you have terminal cancer, and then living with the regret of "if only I got it checked out earlier".
In the engineering world, you are almost always rewarded for being extra safe and testing, fixing, and investigating anything that might seem a little off. If you do blood tests, MRIs, and cancer screens for every mole, cough, and stomach pain, you will go insane and develop hypochondria.
I guess depends on the mental counter response those engineers take. Because you have to think about every possibility, you create a counter temperment that doesn't implode thinking about every possibility.
Some might go the other way, and their anxious personality might help them think about everything, but also make them a stress case.
I think the first type tends to last longer in the industry, at least for my coworkers.
you're conflating "pushing for further tests" with "pushing for further treatment.' IMO, everyone should be entitled to as much data accumulation as they want. Insurance companies can set reasonable thresholds, but if I want to pay out of pocket to get bloodwork done, that should be easy to get.
Whether or not a doctor prescribes/advises a certain treatment is still firmly in their domain. The amount of biomarkers/biological evidence a patient has shouldn't sway a doctor's decision to alter a treatment plan. As a reasonably smart non-medical professional, I would rather have more data than less data, and it's paternalistic and a little condescending to say "no, you shouldn't actually take diagnostic tests because 'having that information might freak you out'"
I wonder if the psychological stress you describe is a result of societal expectations, which itself is a result of what has been done historically. I would think that to most people you are either healthy, or you have a problem, because that is often how it is viewed when it comes to healthcare. In the same way your doctor could say "you are a little overweight, and let's keep an eye on it to make sure it doesn't cause problems down the road", a similar perspective could be had for what people commonly associate with more serious issues. You can look at what the correlations say for health policy, or you can consider the actual reasoning as to why people view healthcare as such in the first place. It's normalized for people to not go to a doctor unless they have a problem, it's normalized to not take regular preventative measures and screenings. In addition, there are financial barriers. While insurance companies may benefit in the long run from more regular, personalized, preventative care, they are likely very resistant to paying for it. With the costs of healthcare, only well off people would consider this approach, as most of their costs may be out of pocket because they don't have a problem to point to for these kinds of screenings. Like getting blood work done maybe every 6 months just to make sure everything is doing ok, hormones, etc. If it was normalized, and people less afraid of the doctor, needles, and of the costs attached to being unhealthy, their sources of psychological stress would likely be non-existent.
I have no expertise here but I worry that these trials are studying the decision-making processes around how people decide to use the information from these tests, rather than the tests themselves.
How people use information varies, so the data might not have external validity - it’s culture specific, and cultures differ. Cultures can also change through accumulated experience.
So do the people studying these things try again with different and possibly better decision-making, or do they conclude that the test itself is no good?
That is a very important point. This is why multiple studies are needed that across time, location, culture, etc. The more data a doctor has the better decisions they can make for their specific patients.
That statement alone shows blatant ignorance of basic properties of the human psyche which makes reading the rest of your long reply rather pointless, as thought-through as it might have been from your perspective.
Humans are not the perfectly rational machines you seem to make them out to be. You need to deal with people in the real world, not some dream utopia that does not exist.
In my particular field of biomedical research, there has recently been a push for "Diagnostic Stewardship" because more information has demonstrably been harmful to patient well-being.
I believe that's what the data says, but I have a really hard time reconciling it with common sense. More information is strictly better than less information, because you can always choose to ignore the extra information.
I would say most medical decisions are made either due to statistics, or due to experience. What treatment has the highest chance of making the patient better, extending their life, or giving the best quality of life? You'd "just" have to adjust the tables for the new test.
I mean in a contrived example, you could have the lab technician themself look up the numerical result (xyz > 100, abc < 10 whatever) in some table, and then there would be the rule to throw the result in the bin and report "don't treat" because this results in the best outcomes. I don't want to have all that extra diagnostic information, but I want my doctors to use it conditionally to improve my treatment if possible.
"I believe that's what the data says, but I have a really hard time reconciling it with common sense."
Can you see why some people might be hesitant about basing medical treatment on "That's what the data says, but it doesn't conform to my priors, so it's probably wrong"?
People are terrible at ignoring information. Clinicians are people. We know this.
> you can always choose to ignore the extra information.
Can you?
That is to say: you can try, but I don't think most people are very good at consciously choosing not to think or worry about something that they know, if that's even possible.
It’s not enough to say it’s harmful. How is it harmful? A blood test, for example, cannot be inherently harmful. (Okay, no more harmful than drawing blood). So it must be about what people then decide to do based on that test. That’s what my post is about.
Do enough of them, and even basic blood tests cause harm. Infections happen. Rupturing veins happens.
If your tests are for conditions that are rare enough, and where early detection does little enough to improve outcomes, even a tiny risk like that becomes a problem.
I should say, if you know ex ante that certain results are not worth acting on, then when you actually get those results ex post, you should ignore them just the same. So actually running a test cannot formally be the problem.
That is not how medicine works, especially with cancer. Very often we simply don't know whether or not to "ignore" something. But the harms of knowing are not zero, and therefore screening can itself be a net negative. That's why a well powered RCT is required to say whether it benefits patients or not.
We have a more detailed exchange going on elsewhere in this thread, with my latest comment, addressing your more detailed points, here: https://news.ycombinator.com/item?id=27630947
Isn't the only way to learn what things we can ignore and what things we can't ignore to do a lot more testing? Is there a better way to learn that? It seems like having a lot more data from tests is the kind of thing that would have some short term harm but massive long term benefits.
if you take dumb patients as the problem, you are willing to hurt people with good decision making ability (who would heed their good doctor’s advice to leave the possible ailment untreated) so you can protect people with bad decision making.
It seems like we've made this decision with covid-19. Dr. Fauci has been canonized, but we know that he's been intentional misleading the public through misinformation (starting from telling us that masks aren't effective in order to preserve the supply for medical providers, and later mis-stating herd immunity numbers to manipulate people into getting the behavior he wanted).
“ If finding something that otherwise carries no symptoms is best left untreated, then the fact that you found it should make no difference to the decision.”
This is easy to say but hard to do, just need to imagine
If I can step in with a personal anecdote: I was diagnosed in my late 20s with papillary thyroid cancer.
PTC is a very survivable cancer, with a near-100% survival rate (death usually only occurs in rare cases where the disease is diagnosed very late, the progession is atypical, or there are comorbidities at play). It is very easy to screen for and diagnose: a neck ultrasound identifies thyroid nodules, and if the nodules look suspicous they are biopsied in a 20 minute procedure performed under local anaesthetic.
Treating papillary thyroid cancer is also relatively straightforward, as far as cancer goes: depending on the size of the lesion and the features, either half or all of the thyroid gland is removed surgically. In cases where the whole gland is removed (which is the majority), the patient is given a course or two of radioiodine therapy to nuke anything left over, and in many/most cases, it's a done deal.
The vast majority of thyroid cancer survivors have to take thyroid replacement hormones (all patients who had the whole gland removed have to do this, and about half of patients who only had half the gland removed still need a small dose to keep up). I'm relatively lucky: the oral hormone seems to work just fine for me. I take a pill every morning and then go about my day. I will need to do this for the rest of my life, but hey, that's life.
However, there's a substantial minority of patients who aren't so lucky: even with oral hormone replacement, they suffer from long-term sequelae including weight gain, low energy, brain fog, hair loss, and other hypothyroid symptoms.
And there lies the crux of the issue: it turns out that even with increased diagnostic capability (thanks to the ubiquity of relatively cheap ultrasound exams in clinical practice), the number of people dying from thyroid cancer has stayed pretty much flat for decades (mostly due to more aggressive types than papillary, such as medullary or anaplastic). Yet, we take out a lot more thyroids now.
The reason this happens is pretty simple: if you see something, you have to do something about it. So you're removing thyroid glands from people where the cancer might never have actually grown big enough to be a problem, and then subjecting those people to a lifetime of hormone replacement therapy. Something like 10% of all cadavers at autopsy have thyroid cancer: it's a cancer that very commonly develops, but only becomes a concern in a few patients. As of now, we don't have a good way to differentiate between "thyroid cancer that's a problem" and "thyroid cancer that'll be fine."
The clinical guidelines have changed a bit in recent years: if the cancerous nodule is really small, they'll now do "watchful waiting" and monitor the nodule to see if it grows. But you're still subjecting a patient to potentially many years of worry and regular testing. And good luck getting life insurance if you have a microcarcinoma! Yeah, it's highly unlikely to kill you (especially when monitored), but try telling an insurer that.
The medical profession is well aware of these concerns. That's why they avoid testing for thyroid cancer unless there are symptoms, such as thyroid hormone disturbances or a lump in the neck. If you were to make a thyroid ultrasound a regular test, you'd quickly overwhelm the system with cancer patients who probably never needed to be treated in the first place, and who may now have to get their thyroids removed and be dependent on pills for the rest of their lives.
But this really just illustrates a lack of knowledge on our part. If we made thyroid screening a regular thing and invested $10B/year into diagnostics, analysis, and study, i guarantee you in 5 years or less we would have the most efficient, effective system for treatment, determining which microcarcinomas are bad, which ones to keep an eye on, etc.
There simply isn't a profit motive right now, and there aren't a ought resources, so unprofitable, minor things like thyroid cancers and other, small, mostly non-fatal things fall by the wayside. If we could massively increase the resources and time spent of solving health issues, we'd have a lot better solutions. There only exist a certain amount of cancer researchers, oncologists, and clinical pharmacologists that can profitably exist. Lots of diseases will never be cured because there are too few people affected by them. Until we decouple medical progress from profit, there's a only a certain amount of progress we can make. Unfortunately, it seems like tying profit to medicine is the most efficient system we have, so it may be centuries till we get there
My thinking is that the tool was not the problem, it was the decision to do something. With what you say about how common and insignificant is often is, then the right choice in a lot of cases is to probably monitor, seeing how much it grows over time. This isn't a cost effective solution if the ultrasounds are expensive or not high resolution enough, or if insurance won't allow you to take this strategy. If there's no benchmarks or thresholds of size or growth of the tumor before cutting it out should be considered, then you are right, it would likely overwhelm the system with uneccessary treatments. The monitoring doesn't feel like the problem to me, it's the decisions/recommendations of the doctor, often being made as a result of professional wisdom, what research was financed, and the financial system that encompasses healthcare.


If finding something that otherwise carries no symptoms is best left untreated, then the fact that you found it should make no difference to the decision. The doctor should say that the best course of action is to do nothing. More information can never be harmful. If you know information is best not acted on in the abstract, then you also know you should not act on it in particular.
So what you really mean but have left unspoken is one of two things.
First, that doctors are untrustworthy people who make recommendations and decisions based on concerns other than their patient’s wellbeing, such as covering their asses from lawsuits or making more money.
But rather than fix that, you would rather keep patients more ignorant and away from the doctor in the first place. Which actively harms people who do have honest doctors. That is, your approach of not testing hurts people with honest doctors to protect people with dishonest doctors.
Or second, if you take dumb patients as the problem, you are willing to hurt people with good decision making ability (who would heed their good doctor’s advice to leave the possible ailment untreated) so you can protect people with bad decision making.
Because many times, these tests will uncover things that obviously need treatment. They will save many lives. But because more stupid people will hurt themselves, then no one should have access to them.
The political and moral assumptions built into these positions are immense and yet the medical field tucks those away and pretends that this is just a purely scientific truth, that someone running more harmless tests is actually inherently harmful.
That is a lie! And a very nasty one at that.